
Tetracycline Derivatives: Doxycycline and Minocycline Compared
Battle of Tetracyclines: How They Actually Work
Imagine a microscopic duel: tetracycline molecules slip into bacterial ribosomes, blocking tRNA attachment and halting protein assembly. This bacteriostatic strategy buys the immune system crucial time to swiftly clear infection.
Chemical tweaks change behavior: doxycycline favors stable absorption and wide tissue distribution, while minocycline’s greater lipophilicity enhances central nervous system and intracellular penetration, influencing clinical use, often guiding antibiotic selection.
In action both are primarily bacteriostatic, though high concentrations can appear bactericidal; resistance arises via efflux pumps and ribosomal protection proteins, so judicious use and dosing preserve efficacy over time.
| Aspect | Primary Effect |
|---|
| Ribosome binding | Blocks tRNA entry → halts protein synthesis |
Where Doxycycline Shines and Minocycline Excels
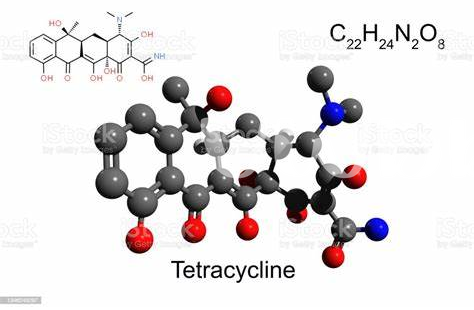
Clinicians often reach for doxycycline for respiratory, skin and tick-borne infections; its reliable oral absorption, long half-life and predictable pharmacokinetics make it a versatile tetracycline with minimal CNS entry.
Minocycline's lipophilicity yields superior tissue and CNS penetration, aiding chronic acne and neurologic infections; anti-inflammatory effects add benefit, though vestibular and pigmentary side effects require caution.
Choosing between them hinges on infection site, patient age, pregnancy status, and adverse-effect profile; doxycycline for broad outpatient use, minocycline when CNS or deeper tissue penetration and anti-inflammatory action are priorities, with stewardship considerations essential.
Dosing Differences, Absorption, and Tissue Penetration
When doctors choose between doxycycline and minocycline, small dosing quirks can change outcomes. Doxycycline often uses once- or twice-daily regimens with predictable levels, while minocycline's longer half-life allows less frequent dosing but requires caution in renal impairment.
Absorption varies: food and divalent cations like calcium can blunt uptake—taking pills with water and away from dairy preserves efficacy. Doxycycline is less affected by food than older tetracycline agents, improving adherence.
Tissue penetration tells another story. Minocycline is lipophilic, crossing into the CNS and skin more readily, which can be advantageous for acne and neurologic infections.
Clinicians balance pharmacokinetics with side-effect profiles and patient factors, tailoring dose and timing to maximize tissue exposure where it’s often needed most.
Side Effects Spotlight: Neuro, Skin, and Teeth

A patient recounts sudden dizziness after starting a tetracycline derivative and the story illustrates neurologic risks. Minocycline more commonly causes vestibular symptoms such as vertigo and imbalance, whereas doxycycline usually produces milder headaches. Rarely, either drug can trigger intracranial hypertension requiring prompt evaluation. Clinicians should ask about balance changes.
Skin effects range from doxycycline photosensitivity that causes exaggerated sunburn to minocycline linked hyperpigmentation and rare autoimmune like syndromes. Both agents can provoke urticarial or morbilliform rashes. Timing and morphology help determine whether to stop therapy or manage with supportive measures and follow up.
Tetracycline class deposition in forming teeth causes staining and enamel defects, so these drugs are contraindicated in pregnancy and children under eight. Adult dental risk is low but counseling is prudent. Weigh risks against benefits, monitor adverse signs, and switch agents when harms appear.
Special Situations: Pregnancy, Kids, and Elderly
When facing infections in pregnancy and childhood, clinicians tread carefully. Classic tetracycline risks—permanent tooth staining and bone growth inhibition—make doxycycline and minocycline generally avoided in pregnancy and in children under eight, except when no safe alternatives exist. In practice, obstetric and pediatric teams weigh maternal benefit against fetal or developmental harm, using narrow indications, shorter courses, and firm counseling.
Older adults present different trade-offs: better tissue penetration and anti-inflammatory effects of doxycycline or minocycline can help chronic infections or dermatologic conditions, but age-related renal or hepatic impairment, polypharmacy, and dizziness risk with minocycline demand dose adjustments, drug interaction checks, and fall-risk mitigation. Shared decision-making, assessment of comorbidities, renal and liver function monitoring, and antibiotic stewardship guide safer prescribing; when risks predominate, clinicians favor alternatives or shorter regimens while documenting rationale and follow-up and involve caregivers in adherence and symptom tracking.
| Population | Typical recommendation |
|---|
| Pregnant | Avoid tetracyclines unless essential |
| Children <8 | Avoid; consider alternatives |
| Elderly | Adjust dose; monitor renal/hepatic function |
Resistance Patterns, Stewardship Tips, and Research
Clinicians watch shifting susceptibility closely; doxycycline and minocycline face different selective pressures. Community-acquired strains often remain vulnerable, but hospital isolates and agricultural exposure can erode effectiveness. Molecular mechanisms—efflux pumps, ribosomal protection proteins, and enzymatic modification—explain why phenotypes diverge regionally. Local antibiograms are invaluable tools for empiric choices.
Practical stewardship balances individual benefit against community risk: narrow-spectrum use, de-escalation guided by cultures, and avoiding routine prophylaxis in low-risk scenarios preserves activity. Dose optimization and shorter courses where evidence supports them reduce selection pressure without compromising outcomes. Education for prescribers and public reduces inappropriate demand.
Emerging studies explore novel derivatives, combination strategies, and rapid diagnostics to tailor therapy faster; surveillance networks help map trends so guidelines can adapt. Clinician curiosity and rigorous trials remain essential to keep these drugs effective for future patients. Funding for translational research speeds bench-to-bedside advances urgently globally.